
Comprehensive Spine Care
Comprehensive Spine Care Guide
A single hub for anyone dealing with neck pain, back pain, a spinal disorder, or a spinal injury organised into seven areas so you can go as deep as you need. Educational content only; see Book a Consultation at the end of the page.
The 7 Pillars of Spine Care
Spine Conditions
What diseases and disorders affect the spine
Symptoms & Warning Signs
What symptoms mean, and which to never ignore
Spine Treatments
From medication and physiotherapy to surgery
Spine Procedures & Surgeries
Detailed explanations of every operation
Prevention & Spine Wellness
Practical, everyday steps to protect your spine
Investigations & Diagnosis
How spine problems are actually diagnosed
Patient Resources
FAQs, reviews, articles & further reading
🩺 Exam before imaging
Diagnosis always starts with a clinical assessment, not a scan.
🧭Surgery-last philosophy
About 90% of spine problems are managed without an operation.
🎯Minimally invasive first
Keyhole, endoscopic and robotic options where suitable.
Why Spine Health Matters
Spine problems are one of the biggest, most under-discussed public health issues in the world – the reason spine awareness deserves the same attention as heart health or stroke prevention.
#1
619M+
~60–66%
50–54
Part 1
Spine Conditions
What diseases and disorders affect the spine
Understanding Your Spine
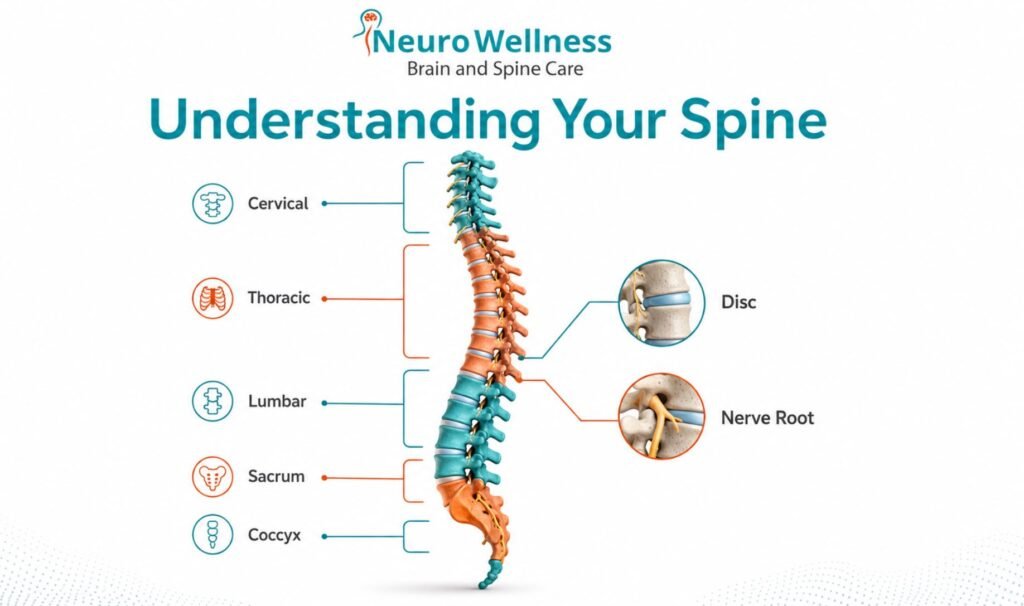
The spine is a stacked column of 33 vertebrae running from the base of the skull to the tailbone, divided into five regions: cervical (neck, 7 vertebrae), thoracic (mid-back, 12 vertebrae), lumbar (lower back, 5 vertebrae), sacrum, and coccyx. Between the vertebrae sit shock-absorbing discs; behind them runs the spinal canal, housing the spinal cord and nerve roots; facet joints guide movement, and ligaments and muscles stabilise the whole column.
Beyond housing the spinal cord, the spine provides structural support, protection, movement, shock absorption, and balance. Because it is under continuous mechanical load throughout life, gradual wear is normal, an MRI finding alone doesn’t always mean disease.
Common Spine Conditions
For the complete in-depth reference, see Spine Conditions & Disorders: A Complete Guide.
Slip Disc (Disc Prolapse)
Disc centre pushes through its outer wall and presses on a nerve
Cervical Spondylosis
Age-related osteoarthritis of the neck
Lumbar Spondylosis
Age-related osteoarthritis of the lower back
Sciatica
Pain radiating from the back through the leg.
Spinal Canal Stenosis
Narrowing of the canal squeezing the cord or nerves
Scoliosis
Abnormal sideways curvature of the spine
Kyphosis
Excessive forward rounding of the upper back
Spondylolisthesis
One vertebra slipping forward over another
Spinal Tumors
Primary or metastatic tumours affecting the spine
Spine Infections
Discitis, osteomyelitis, epidural abscess, spinal TB
Osteoporosis- Related Fractures
Compression fractures of weakened vertebrae
Spinal Cord Compression
Pressure on the cord itself – clumsy hands, unsteady gait
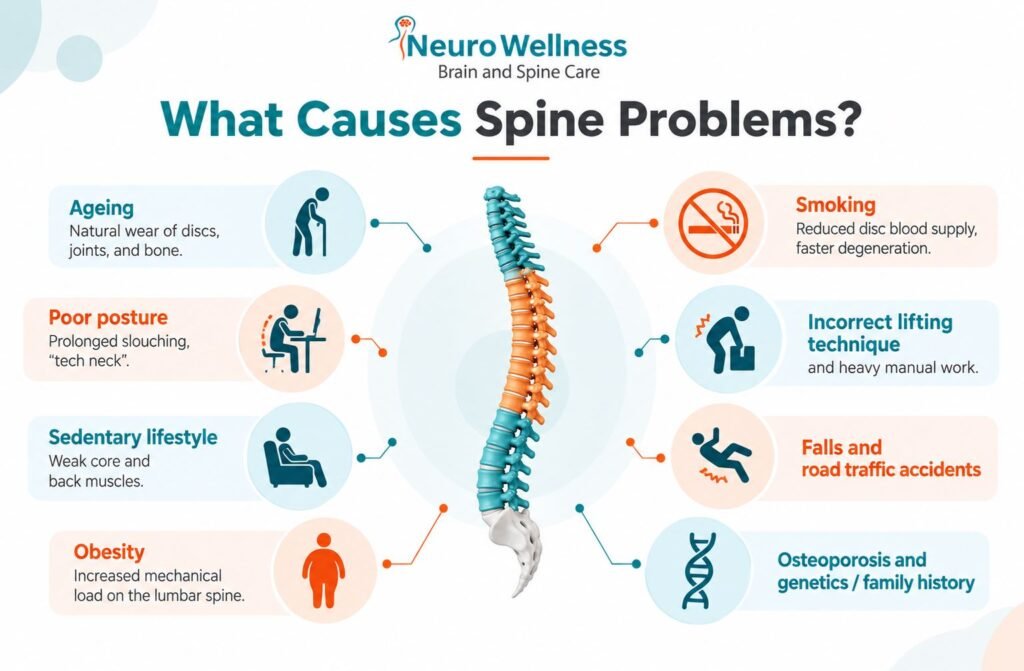
What Causes Spine Problems?
- Ageing – natural wear of discs, joints, and bone
- Poor posture – prolonged slouching, “tech neck”
- Sedentary lifestyle – weak core and back muscles
- Obesity – increased mechanical load on the lumbar spine
- Smoking – reduced disc blood supply, faster degeneration
- Incorrect lifting technique and heavy manual work
- Falls and road traffic accidents
- Osteoporosis and genetics/family history
Part 2
Symptoms & Warning Signs
What symptoms should people never ignore?
Symptom Checker
Most people arrive here trying to understand what they’re feeling, not for a diagnosis. Start here — items marked ⚠ are potential red-flag symptoms.
Any ⚠ item – see Emergency Warning Signs below and seek care immediately.
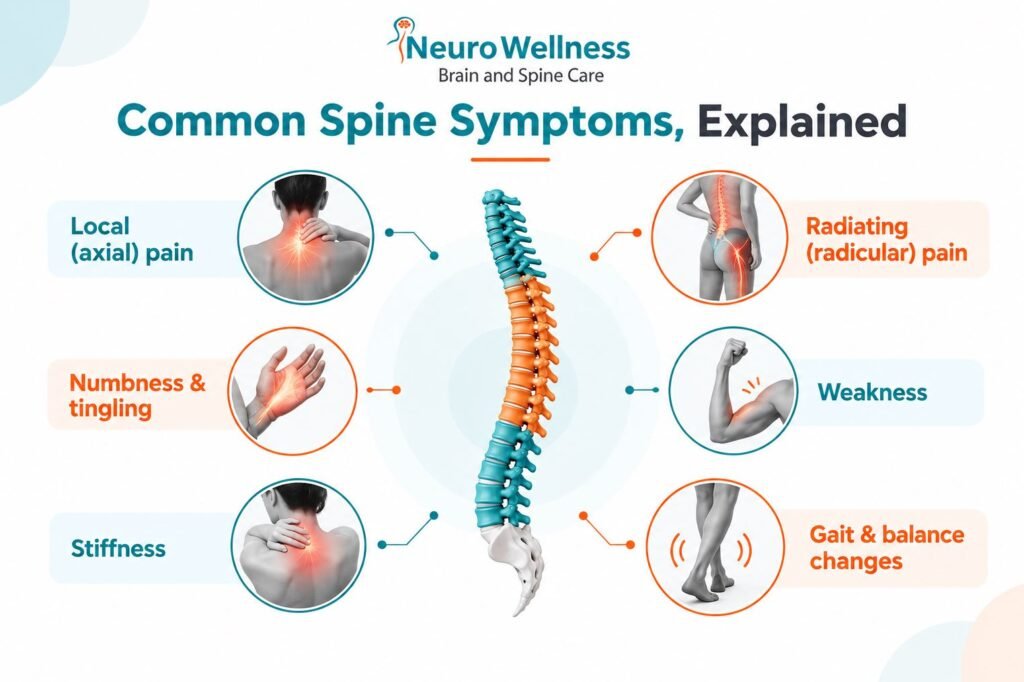
Common Spine Symptoms, Explained
Most people arrive here trying to understand what they’re feeling, not for a diagnosis. Start here — items marked ⚠ are potential red-flag symptoms.
Local (axial) pain
Confined to the neck or back usually muscular, ligament or joint-related.
Radiating (radicular) pain
Travels down an arm or leg usually a compressed nerve root, e.g. sciatica.
Numbness & tingling
Follows a nerve path; helps localise the affected level.
Weakness
Grip difficulty or foot drop needs prompt review.
Stiffness
Morning stiffness that eases with movement can suggest inflammatory arthritis.
Gait & balance change
Clumsy hands or an unsteady walk may indicate spinal cord compression - see a specialist.
Sciatica — A Closer Look
What it is: pain following the sciatic nerve from the lower back, through the buttock and down one leg. It is a symptom, not a diagnosis in itself.
Common causes: herniated / bulging lumbar disc (most common), lumbar spinal stenosis, spondylolisthesis, piriformis syndrome.
How it typically feels: usually one-sided; burning, shooting or electric-shock-like; often worse with sitting, coughing or straining; may include numbness, tingling or weakness.
How it’s treated: most episodes improve within weeks with staying active, anti-inflammatory medication and physiotherapy. Surgery usually microdiscectomy is reserved for severe persistent pain or red-flag features.
When to be more concerned: progressive leg weakness, saddle numbness, or new bladder/bowel symptoms – see Emergency Warning Signs.
Emergency Warning Signs — When Not to Wait
Seek emergency care immediately if you experience:
- New loss of bladder or bowel control
- Numbness in the “saddle” area (inner thighs, buttocks, groin)
- Rapidly worsening weakness or numbness in one or both legs, or sudden paralysis
- Severe neck / back pain after major trauma
- Back / neck pain with fever, unexplained weight loss, or a cancer history
- Sudden difficulty walking, loss of balance, or clumsy hands
Part 3
Spine Treatments
Everything from conservative care to surgery
Treatment Options Overview
Most spine conditions respond to non-surgical care. Surgery is a later step, considered when conservative treatment fails or clear indications exist.
Non-Surgical
- Medicines
- Physiotherapy
- Lifestyle modification
- Spine injections (epidural, nerve root block, facet, radiofrequency)
- Rehabilitation
Surgical
- Minimally invasive spine surgery
- Endoscopic spine surgery
- Microsurgery
- Fusion surgery (TLIF/PLIF/ALIF/XLIF)
- Artificial disc replacement
Non-Surgical Treatments in Detail
- Epidural Injection – steroid injected into the epidural space to settle nerve inflammation, commonly used for sciatica
- Nerve Root Block – targeted injection around a specific nerve root, both diagnostic and therapeutic
- Facet Joint Injection – for pain from the small joints connecting adjacent vertebrae
- Radiofrequency Procedures – heat disables small nerves carrying pain from an arthritic facet joint, for longer-lasting relief
- Cervical Collars / Bracing – short-term support, under medical guidance
Understanding Risks & Complications
As with any surgery, spine surgery carries some risk of bleeding, infection, nerve injury or hardware-related issues. Minimally invasive, endoscopic and robotic techniques reduce several of these risks compared with open surgery, but do not eliminate them. A transparent, individualised discussion of risks and benefits is standard practice.
Recovery After Spine Surgery
Day 1
Sit up, walk with assistance
Week 1
Increasing walking, light activity
Month 1
Physiotherapy, most daily tasks
Month 3
Return to office work (typical)
Month 6
Sport/heavy activity reassessed
Part 4
Spine Procedures & Surgeries
Detailed explanations of every operation
Spine Procedures & Surgery - At a Glance
| Procedure | Used for | Approach |
|---|---|---|
| Microdiscectomy (MLD) | Sciatica from a lumbar disc herniation | Minimally invasive |
| Endoscopic discectomy | Disc & nerve compression | Keyhole / day-care |
| ACDF / Cervical disc replacement | Cervical disc disease, nerve / cord compression | Front-of-neck |
| TLIF / PLIF / ALIF / XLIF | Lumbar instability, spondylolisthesis | Fusion (by approach) |
| Laminectomy / Laminoplasty | Spinal canal stenosis | Decompression |
| Vertebroplasty / Kyphoplasty | Osteoporotic compression fractures | Cement stabilisation |
Spine Procedures – Complete List
Non-surgical
- Physiotherapy and structured exercise therapy
- Epidural steroid injection (ESI)
- Facet joint injection
- Selective nerve root block (SNRB)
- Sacroiliac (SI) joint injection
- Radiofrequency ablation
- Cervical collar / lumbar bracing (short-term)
Surgical
- Microdiscectomy (MLD)
- Endoscopic discectomy
- ACDF
- Cervical Disc Replacement — motion-preserving alternative to ACDF
- TLIF
- PLIF
- ALIF
- XLIF
- Laminectomy, Laminoplasty, Foraminotomy
- Vertebroplasty / Balloon Kyphoplasty
- Spinal Fixation & Instrumentation
- Corpectomy
- Tumor Surgery & Spine Trauma Surgery
- Scoliosis / Deformity Correction Surgery
- Robotic-assisted & navigation-guided spine surgery
Minimally Invasive, Robotic & Endoscopic Spine Surgery
Minimally Invasive (MISS)
Small incisions and tubular retractors preserve surrounding muscle.
- Less blood loss & pain
- Shorter hospital stay
- Faster return to work
Robotic Spine Surgery
A 3D surgical plan guides a robotic arm for millimetre-accurate screw placement. It assists – it does not operate independently.
- Greater implant accuracy
- Fewer revision surgeries
- Many walk the same day
Endoscopic Spine Surgery
An HD scope through an incision often under a centimetre treats discs and nerve compression.
- Often day-care / single-night stay
- Low blood loss
- Early return to function
Microdiscectomy
One of the most frequently performed and successful spine surgeries — the standard treatment for sciatica from a lumbar disc herniation unresponsive to conservative care.
| Treats | A herniated lumbar disc pressing on a nerve root, causing persistent leg pain, numbness, or weakness despite approximately 6 weeks of conservative treatment. |
|---|---|
| How it’s done | A 2–3 cm incision is made. An operating microscope is used with gentle muscle retraction, and only the disc fragment pressing on the nerve is removed. |
| What to expect | Often performed as a day-care procedure or with a single-night stay. Walking is usually possible the same day. Desk work may resume in 2–4 weeks, while heavy lifting is generally restricted for 6–8 weeks. |
| Risks | Infection, bleeding, dural tear, and a small chance of disc recurrence at the same level. |
TLIF & PLIF (Lumbar Interbody Fusion) — Explained in Detail
TLIF & PLIF
The two most common techniques for lumbar spinal fusion joining vertebrae to eliminate painful / unstable movement and relieve nerve compression.
| Treats | Spondylolisthesis, lumbar stenosis with instability, recurrent disc herniation, degenerative disc disease with instability. |
|---|---|
| TLIF | Approach from one side through the neural foramen — less nerve retraction. |
| PLIF | Approach from the back on both sides — slightly more retraction. |
| What to expect | 2–4 day stay (shorter with MISS / robotic); walking from day one; fuller activity guided by fusion confirmation over 3–6 months. |
| Risks | General risks plus hardware complications, non-fusion, and long-term adjacent-segment stress. |
ALIF & XLIF — Explained
ALIF & XLIF
Two further lumbar fusion techniques, distinguished by the direction of surgical approach.
| ALIF | Anterior Lumbar Interbody Fusion — through a small lower-abdomen incision to reach the disc space, most often L5–S1 or L4–5. Avoids the back muscles and nerves and allows a larger implant to restore disc height and lordosis. Often performed with a vascular access surgeon. |
|---|---|
| XLIF | Extreme / Lateral Lumbar Interbody Fusion — from the patient’s side through the psoas muscle, with continuous nerve monitoring. Allows a large cage and is often combined with posterior screws. Temporary thigh numbness or weakness is possible and usually settles over weeks. |
| Choosing | Depends on the spinal level, patient’s anatomy, and surgeon’s assessment — there is no single “best” approach for every patient. |
Other Spine Procedures
- Laminectomy — removes part of the lamina to relieve spinal canal stenosis
- Laminoplasty — reshapes rather than removes the lamina (cervical spine)
- Foraminotomy — enlarges the nerve exit tunnel
- Vertebroplasty / Balloon Kyphoplasty — cement stabilisation of osteoporotic fractures
- Spinal fixation & instrumentation — screws, rods, plates; often navigation / robot-guided
- Corpectomy — vertebral body removal with reconstruction
- Tumor & spine trauma surgery — from biopsy or stabilisation to complex resection and fixation
Part 5
Prevention & Spine Wellness
Practical, everyday steps to protect your spine
Building a Lifelong Healthy Spine
- Healthy Weight: Reduces mechanical load on the lumbar spine
- Core Strengthening: Planks, bridges, pelvic tilts 3–4x/week
- Spine Exercises: Stretching, core work, low-impact cardio
- Bone Health: Calcium, Vitamin D, weight-bearing exercise
- Weight Reduction: Even modest loss reduces lumbar load
- Avoid Smoking: Smoking accelerates disc degeneration

Spine Wellness at Work
Ergonomics & Office Sitting Posture. An ergonomic workstation – screen at eye level, feet flat on the floor, lumbar support with a movement break every 30–45 minutes makes a measurable difference for Bengaluru’s desk-bound IT and corporate workforce.
Mobile Neck Prevention (“Tech Neck”). Holding the phone at eye level where possible, and taking frequent breaks, reduces neck strain from prolonged phone use.
Workplace Spine Care. Structured ergonomics assessments and spine-awareness sessions for organisations can reduce absenteeism linked to musculoskeletal complaints.
Everyday Spine Habits
- Correct Mattress: Medium-firm, supporting the spine’s natural curve; an old, sagging mattress is an under-recognised cause of morning stiffness.
- Correct Pillow: Keeps the neck neutral; side sleepers generally need a thicker pillow than back sleepers.
- Driving Tips: Knees level with hips, lumbar support, seat close enough to avoid reaching; break every 1–2 hours.
- Lifting Techniques: Bend at the knees and hips, keep the load close, avoid twisting — one of the most effective injury-prevention habits.
- Diet & Hydration: An anti-inflammatory diet, adequate protein and good hydration support disc health; discs are largely water and lose hydration with age and dehydration.

Part 6
Investigations & Diagnosis
How spine problems are actually diagnosed
How Spine Conditions Are Diagnosed
Exam
History & clinical examination
Imaging
X-ray / MRI / CT / DEXA
Special Tests
EMG, blood work if needed
Diagnosis & Plan
Tailored to the patient, not the scan
Diagnostic Tests Explained
- Clinical Examination — the foundation of diagnosis
- X-ray — bone alignment, stability, degenerative changes
- Dynamic X-rays (Flexion-Extension) — assess spinal stability and abnormal movement between vertebrae
- MRI Spine — gold standard for discs, nerves, spinal cord, soft tissue
- CT Scan — detailed bone anatomy, fractures, surgical planning
- EMG/NCV — nerve and muscle electrical conduction studies
- Bone Density Test (DEXA) — osteoporosis risk assessment
- Blood Tests — used selectively to rule out infection or inflammatory disease
When Is an MRI Needed?
Generally recommended when pain persists beyond a few weeks despite conservative care, when there are neurological symptoms, or when red-flag symptoms are present – not for every episode of ordinary back pain.
Spine Myths vs Facts
Spine health is full of well-meaning but inaccurate advice. Here are some of the most common myths, and what the evidence actually shows.
| Myth | Fact |
|---|---|
| “A slipped disc can be put back in place.” | A disc doesn’t “slip” out and get pushed back — it bulges or herniates, and the body reabsorbs the extruded material over time with the right care. |
| “Bed rest is the best cure for back pain.” | Prolonged bed rest actually slows recovery. Staying gently active is consistently better for most back and neck pain. |
| “If my MRI shows a bulge, I need surgery.” | Disc bulges are extremely common even in people with no pain at all. Surgery is guided by symptoms matching the scan, not the scan alone. |
| “Cracking your back or neck causes damage.” | Occasional, gentle self-cracking is not known to cause harm in healthy people – though it doesn’t “fix” anything structural either. |
| “Once you have back pain, it never fully goes away.” | Most episodes of back pain resolve within weeks with appropriate care, and recurrence risk can be meaningfully reduced with core strength and good habits. |
| “Surgery is always the first option for a herniated disc.” | The large majority of disc herniations are treated successfully without surgery it’s reserved for a minority who don’t improve or who have clear warning signs. |
Part 7
Patient Resources
Education and engagement
Related Articles
Frequently Asked Questions About Spine Care
Degenerative disc disease, herniated discs, spinal stenosis, and spondylosis are most common, followed by deformities, fractures, and less commonly tumours and infections.
Yes. Most back pain, sciatica, and early degenerative disc disease improve with physiotherapy, medication, posture correction, and lifestyle changes.
Microdiscectomy removes a disc fragment without fusion. ACDF fuses cervical vertebrae via a front-of-neck approach. TLIF, PLIF, ALIF, and XLIF are lumbar fusion techniques distinguished by approach direction – one side of the back, both sides of the back, the front of the abdomen, or the side through the psoas muscle.
An approach using small incisions and specialised retractors that preserve surrounding muscle, typically resulting in less pain and faster recovery than open surgery.
Robotic guidance improves accuracy of screw and implant placement. The robot assists and guides the surgeon — it does not operate independently.
No. Most back pain is due to muscle strain and settles within a few weeks. Persistent pain or red-flag symptoms should be evaluated.
Many patients can – most disc herniations and much of chronic back pain respond well to physiotherapy, posture correction, and targeted exercise.
Both treat spine conditions. A neurosurgeon’s expertise is particularly valuable when nerve or spinal cord involvement is suspected.
Look for fellowship training in minimally invasive, endoscopic, and robotic-assisted techniques, a willingness to explain non-surgical options first, and transparent discussion of risks.
More questions are answered across our spine resources and each condition guide.
What patients say
I had consulated dr ganesh Veerabhadra iah best Neuro and spine doctor i was suffering from severe backpain after consulting him now I’m recovering well special thanks doctor and his team
— Silambu Army, Google
Dr.Ganesh Veerabadriah (Neurosurgeon ) the best ,service minded and dedicated person
Hus hard work leads to good personality of the patients health
May god give him more knowledge and wisdom in his career er towards the patients as well for his family members
Thank u sir for ur lovable service to umy mom.
— Jansi shaan, Google
Very patient centric, humble, having essential professional acumen.
Planned my ACDF meticulously.
I understand, he will be of much help to me!
— Vinay Upadhyay, Google
Book a Consultation
If you are dealing with neck pain, back pain, sciatica, a slipped disc, or have been advised to consider spine surgery, an accurate diagnosis and a clear conversation about your options is the recommended next step.
Medically reviewed by Dr. Ganesh Veerabhadraiah, HOD and Senior Consultant Neurosurgeon, NeuroWellness, Bengaluru. Last reviewed: 15-Oct-2026
Disclaimer: This content is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Please consult a qualified specialist for guidance appropriate to your condition. Do not use this information for self-diagnosis or self-treatment. In a medical emergency, seek immediate care at the nearest hospital. NeuroWellness does not promote, endorse or recommend any particular doctor or procedure.