
NEUROWELLNESS · SPINE CARE, BENGALURU
TLIF Lower Back Surgery, Explained Simply
Lower back pain that travels down your leg? A slipped vertebra? Pain that gets worse every time you stand or walk? An unstable or worn-out disc may be pressing on your nerves. TLIF is the most common modern lumbar fusion here is everything you need to know, in plain, everyday language.
TLIF at a glance
- Where Lower back, approached from one side of the back
- Why Free trapped nerves and stabilise a loose segment
- Walk Usually on day 1–2
- Stay About 2–4 days in hospital
- Work Desk work in about 8–12 weeks
- Fusion Bones join solidly in 3–6 months
The name, decoded
What is TLIF?
TLIF stands for Transforaminal Lumbar Interbody Fusion. It sounds complicated, but each word simply tells you what the surgeon does.

Transforaminal
The disc is reached from one side, through the foramen – the small opening where a nerve exits the spine.
Lumbar
The lumbar spine is the five large bones in your lower back that carry most of your body weight.
Interbody
The worn disc is removed and a spacer (cage) is placed in the gap between two vertebrae.
Fusion
The two bones heal together into one solid, stable unit, so the painful movement stops.
Know your lower back
How your lower back is built
- Your lower back has 5 large bones called lumbar vertebrae (L1 to L5), sitting on top of the sacrum.
- Between every two bones sits a disc — a tough cushion that absorbs shock when you walk, bend and lift.
- On each side, a small opening called the foramen lets a nerve root exit the spine and travel to the leg. TLIF uses this opening as its doorway to the disc.
- Inside the spinal canal run the nerves that travel to your hips, legs and feet, and control bladder and bowel.
💡 Think of it like this: your lower spine is a stack of building blocks with rubber pads in between. If a pad wears flat or a block slides forward, the stack becomes wobbly — and the “electric wires” running behind it get pinched.
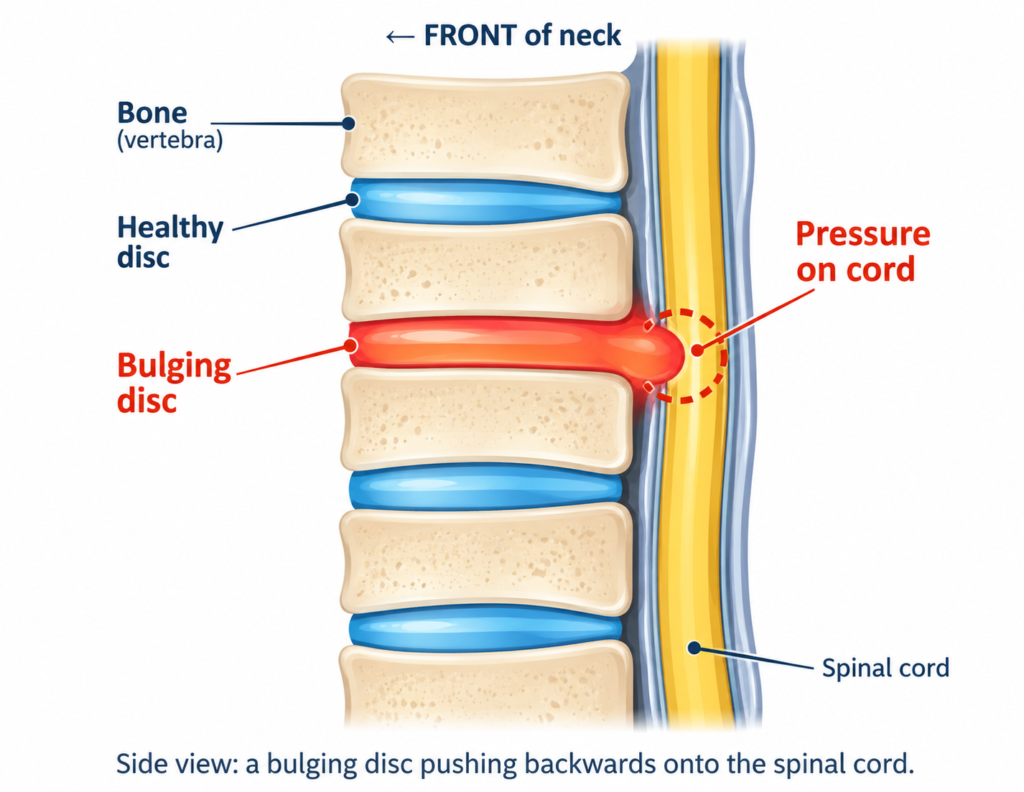
What goes wrong
Conditions treated with TLIF
TLIF is used when a segment of the lower spine has become unstable or the disc has worn out, and the nerves are being squeezed. Common reasons:
↘️ Spondylolisthesis
One vertebra slips forward over the one below, narrowing the nerve space. It may be age-related (degenerative) or due to a small stress fracture (isthmic).
⏳ Degenerative disc disease
From the 40s onwards, discs lose water, flatten and stop cushioning properly, causing pain and nerve pressure.
🔁 Recurrent disc herniation
A disc that bursts again after an earlier operation, especially when the segment has also become loose.
⚖️ Lumbar instability
Excess movement between two bones, seen on bending X-rays, that causes mechanical back pain and leg symptoms.
🦴 Stenosis with instability
Narrowing of the spinal canal or nerve window, combined with a loose segment that needs stabilising.
🎯 One-sided nerve compression
When symptoms are mainly on one side, the one-sided TLIF route lets the surgeon free that nerve directly.
Listen to your body
Symptoms you may notice
- Lower back pain that worsens on standing, bending or lifting and eases on lying down
- Pain that travels down the buttock and leg (sciatica)
- Tingling, numbness or pins-and-needles in the leg or foot
- Heavy, tired legs after walking a short distance, relieved by sitting or bending forward
- Weakness in the leg or foot — tripping or a “slapping” foot
- A feeling that the back is “catching” or giving way
⚠️ Warning signs — seek urgent medical care
These may mean the nerves at the bottom of the spine are severely compressed (cauda equina syndrome). This is an emergency.
- Numbness around the private parts, buttocks or inner thighs (“saddle” area)
- New difficulty passing urine, or loss of bladder or bowel control
- Rapidly increasing weakness in one or both legs
- Severe pain in both legs together
Finding the cause
How is it diagnosed?
A correct diagnosis is the most important step. Not every back pain needs fusion, and not every MRI finding is the cause of symptoms.
🩺 Clinical examination
Strength, sensation, reflexes and walking are checked to find which nerve is affected.
🧲 MRI scan
Shows discs, nerves and the spinal canal clearly, and exactly where the pressure is.
🩻 Standing & bending X-rays
Flexion–extension X-rays show whether a vertebra is slipping or moving abnormally.
🦴 CT scan
Sometimes used to confirm nerve damage and rule out problems like carpal tunnel syndrome.
🧪 Blood tests & bone health
Routine fitness tests, plus bone density checks in older patients, since strong bone helps fusion.
❤️ Fitness check
Heart and anaesthesia assessment to make sure surgery is safe for you.
Surgery is not the first step
Do I really need fusion surgery?
Most people with lower back and leg pain do NOT need fusion. Many improve with the right non-surgical treatment.
✅ Try first: non-surgical treatment
- Pain-relief and nerve-calming medicines
- Physiotherapy and core-strengthening exercises
- Activity changes, posture and lifting technique
- Weight management
- Epidural or nerve-root injections in selected patients
🔧 Fusion may be advised when:
- Leg or back pain continues despite several months of proper treatment
- Imaging shows a slipped or unstable segment that matches your symptoms
- There is increasing weakness or numbness in the leg
- Walking distance keeps shrinking and daily life is badly affected
- A disc has burst again at a level that is already loose
Step by step
What happens during TLIF surgery?
The length of surgery depends on the number of levels treated. Here is what happens, in simple words:
You go fully to sleep
General anaesthesia is given. You feel no pain and remember nothing of the surgery.
You lie face-down and the back is opened
An incision is made over the lower back. In minimally invasive TLIF (MIS-TLIF), small cuts and tube-shaped retractors are used, so the muscles are moved aside rather than stripped.
Live X-ray confirms the level
Real-time X-ray (fluoroscopy) makes sure the correct segment is being treated.
The nerve window is opened on one side
A small facet joint on the more painful side is removed to open the foramen. This frees the trapped nerve and creates the doorway to the disc.
The disc is removed from that one side
The nerve is gently protected while the worn disc is cleared out. Because the approach is from one side, there is less pulling on the nerves than in PLIF.
One cage and bone graft are placed
A single spacer (cage), usually PEEK or titanium and packed with bone graft, is placed diagonally across the disc space to restore its height and start the fusion.
Screws and rods hold everything steady
Pedicle screws are placed into the vertebrae on both sides and joined with rods, acting like an internal splint while the bone heals.
The wound is closed
Over 3–6 months, the two vertebrae grow together through the cage into one solid bone. This is the "fusion".
Healing and fusion over months
Over 3–6 months, the two bones grow together through the cage into one solid bone. This is the "fusion".
The key question
TLIF vs PLIF
TLIF was developed in the 1980s as a refinement of PLIF. Both aim for the same result — a solid, stable segment with free nerves. The right choice depends on your anatomy and the surgeon’s judgement.
| TLIF | PLIF | |
|---|---|---|
| Approach | From one side, through the nerve window (transforaminal) | Directly from the back, on both sides |
| Nerve retraction | Less — lower nerve-irritation risk | More — nerves are moved on both sides |
| Cages | Usually one, placed diagonally | Usually two, one from each side |
| Blood loss & operating time | Generally less / shorter | Generally more |
| Fusion rates & outcomes | Broadly similar between the two | |
| Usage today | Most common lumbar fusion in many centres | Used for specific indications |
Both can be done with open or minimally invasive techniques. See our PLIF page for more detail, or read about minimally invasive spine surgery.
Getting back to life
Recovery timeline
Every patient is different, but here is a typical path after TLIF. MIS-TLIF can make the early weeks easier.
Up and walking
With help from the physiotherapist, most patients sit up and walk within a day or two. Leg pain often improves early.
Going home
Hospital stay is usually 2–4 days, once you can walk safely and pain is controlled with tablets.
Short walks at home
Walking several times a day, light self-care, wound check-up. A brace may be advised for some patients.
Driving and physiotherapy
Driving once you can sit and turn comfortably and are off strong painkillers. Guided physiotherapy begins.
Back to desk work
Office or computer work can usually resume, with breaks to stand and walk.
Solid fusion
The bones join firmly. Heavier activity and physical jobs resume gradually with medical clearance. Full recovery takes several months.
After surgery
Do's and Don'ts
✅ Do
• Walk every day – start small and increase gradually
• Use the “log roll” to get in and out of bed
• Wear the brace only if and as advised
• Keep the wound clean and dry
• Eat well, with enough protein and calcium for bone healing
• Attend all follow-up visits and X-rays
❌ Don’t
• Lift heavy weights or bend and twist at the waist in the early weeks
• Smoke – it badly slows bone fusion
• Sit for long periods without getting up
• Drive while on strong pain medicines
• Return to gym, sport or manual work before you are cleared
• Ignore fever, wound discharge, calf swelling or new leg weakness
Clearing the fear
Common myths vs facts
MYTH
“After fusion, I won’t be able to bend at all.”
FACT
When one or two levels are fused, the rest of the spine and the hips continue to move. Most people return to normal daily activities.
MYTH
“Back surgery causes paralysis.”
FACT
Serious nerve injury is rare. TLIF’s one-sided approach was designed specifically to reduce pulling on the nerves.
MYTH
“I will be bedridden for months.”
FACT
Patients are encouraged to walk within a day or two. Walking is a key part of recovery.
MYTH
“The screws will have to come out later.”
FACT
The screws and rods are usually left in place permanently and do not need removal unless a specific problem arises.
FACT
MIS-TLIF achieves the same fusion through smaller cuts. It can reduce blood loss and ease early recovery in suitable patients.
MYTH
“Every slipped disc needs fusion.”
FACT
Most disc problems settle without surgery, and many that need surgery can be treated without fusion. Fusion is for instability or specific problems.
Honest information
Possible side effects and risks
Possible side effects and risks
Every surgery carries some risk. Your surgeon will discuss your personal risk before any decision is made.
Common, usually temporary
- Pain and stiffness around the wound for a few weeks
- Some leg tingling or numbness that settles as the nerves recover
- Tiredness during the first few weeks
✅ Specific to TLIF: because the nerves are moved on one side only, the risk of nerve irritation is generally lower than with PLIF.
Less common / rare
- Wound infection or bleeding
- Nerve irritation or injury, or a leak of spinal fluid
- Bones not fusing fully (non-union) — more common in smokers and people with weak bones
- Screw or cage loosening or shifting
- Blood clots in the legs
- Extra wear on the levels next to the fusion over the years (adjacent segment disease), which may need treatment in future
Careful patient selection, precise technique, not smoking and following post-operative advice all help keep these risks low.
COMMON QUESTIONS
TLIF FAQs
A lumbar fusion that joins two vertebrae via a one-sided (transforaminal) approach, using a cage, bone graft and screws — for instability, spondylolisthesis or a painful degenerated disc.
Both have similar fusion rates and outcomes. TLIF’s one-sided approach means less nerve retraction and lower nerve-injury risk, which is why it’s now more commonly used; PLIF still suits certain cases.
It’s a fusion, so more involved than a simple discectomy but it can often be done minimally invasively, reducing blood loss and speeding early recovery. Your surgeon will explain what to expect.
It’s a fusion, so more involved than a simple discectomy but it can often be done minimally invasively, reducing blood loss and speeding early recovery. Your surgeon will explain what to expect.
Minimally invasive TLIF uses small incisions and tube-shaped retractors, so the back muscles are moved aside rather than stripped. It may mean less pain and blood loss early on. Not every case is suitable.
No. TLIF is done under general anaesthesia, so you are fully asleep and will not feel or remember the operation.
Many patients notice leg pain easing soon after surgery. Numbness and weakness usually recover more slowly, over weeks to months, depending on how long the nerves were compressed.
Titanium screws and PEEK or titanium cages are generally MRI-safe. Always tell the scan centre that you have a spinal implant.
The fused level does not usually develop the same problem again. Over many years, the levels next to it may wear; staying active, keeping a healthy weight and not smoking help protect them.
When medically necessary, spinal fusion is generally covered by most health insurance policies, subject to your policy terms. Please check with your insurer.
Been advised a lumbar fusion? Get clarity first.
Bring your MRI and reports. We’ll confirm whether fusion is truly needed, explain TLIF vs the alternatives, and what recovery really involves.
Medically reviewed by Dr. Ganesh Veerabhadraiah, HOD and Senior Consultant Neurosurgeon, NeuroWellness, Bengaluru. Last reviewed: 21-Oct-2026
Disclaimer: This content is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Please consult a qualified specialist for guidance appropriate to your condition. Do not use this information for self-diagnosis or self-treatment. In a medical emergency, seek immediate care at the nearest hospital. NeuroWellness does not promote, endorse or recommend any particular doctor or procedure.