
NEUROWELLNESS · SPINE CARE, BENGALURU
Spine Investigations & Diagnosis
How spine problems are really diagnosed — from a proper clinical examination to X-ray, MRI, CT, DEXA and nerve tests. Including the question everyone asks: do I actually need an MRI?
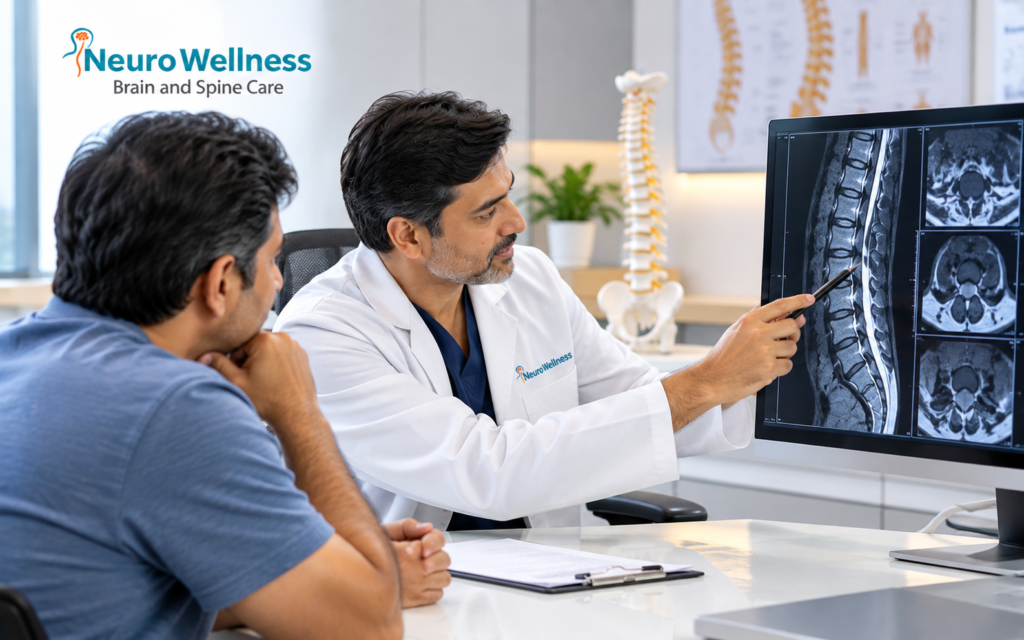
~90%
Of back pain improves in weeks often with no scan needed
>80%
Of pain-free over-60s show disc degeneration on MRI
Exam first
Diagnosis starts clinically — imaging confirms
6 wks
Usual threshold for MRI if pain persists (without red flags)
Start Here
How are spine problems diagnosed?
An accurate spine diagnosis starts with a clinical examination your history and a physical exam not a scan. Tests like X-ray, MRI, CT, DEXA and nerve studies are then chosen only if they’ll change your treatment. The goal isn’t more testing; it’s the right test at the right time, interpreted alongside your symptoms.
Understanding what each test does and doesn’t do helps you avoid unnecessary scans and get to the right answer faster.
🩺 Exam before imaging
A thorough clinical exam decides if, and which, scan is actually needed.
🧲 MRI isn't automatic
Most back pain needs no scan at all in the first few weeks.
📄 Findings ≠ diagnosis
Scan findings only matter if they match your actual symptoms.
💬 Second opinions welcome
Already have a scan? We'll review it against your symptoms first.
The Big Question
Do you actually need an MRI for back pain?
Usually not — at least not straight away. Around 90% of back pain settles within a few weeks with simple care. Scanning too early rarely changes the outcome and can lead to unnecessary treatment. Crucially, MRI is so sensitive that it finds “abnormalities” in people with no pain at all — so a scan finding only matters if it explains your symptoms.
⚠️ Findings are common in pain-free people
On MRI, disc degeneration appears in roughly 20% of pain-free 20-year-olds, 40% of 40-year-olds, and over 80% of over-60s. Disc bulges and stenosis are often seen in people with no symptoms. A finding is not automatically the cause of your pain.
✅ When an MRI is genuinely useful
Imaging is recommended when: pain persists beyond ~6 weeks despite treatment; there's radiating pain, numbness or weakness; or red-flag signs suggest a serious cause (see below). In these cases, an MRI can be very valuable — even life-saving.
Step 1 · Always
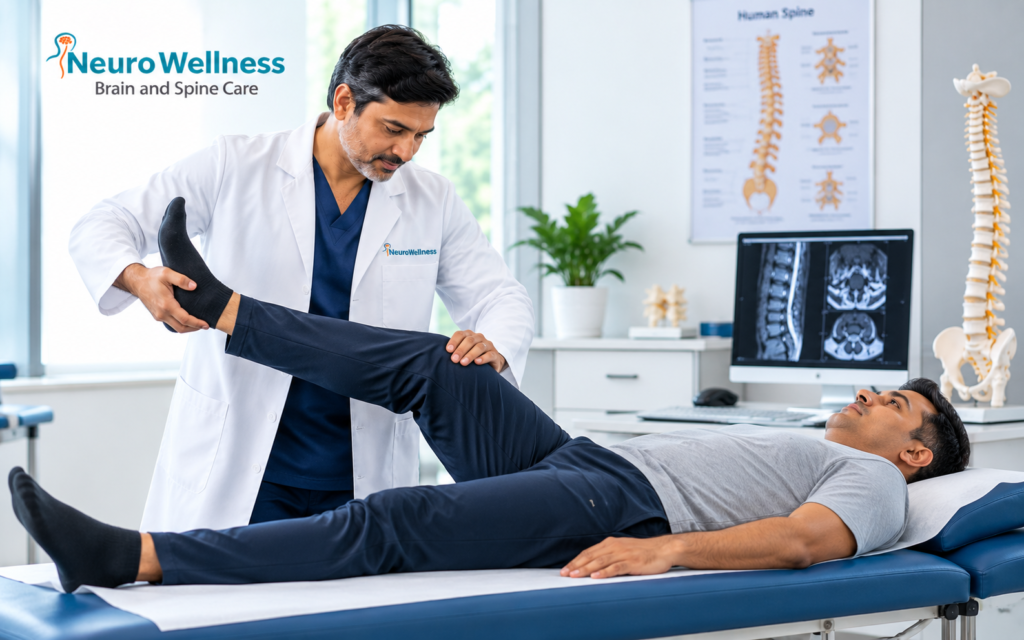
Diagnosis begins with a clinical examination
Before any scan, a spine specialist takes a detailed history (how and where it hurts, what eases or worsens it, any red flags) and performs a physical examination — testing movement, reflexes, sensation, muscle power and nerve-tension signs like the straight-leg raise.
This is what tells the specialist which test — if any — is needed, and how to interpret it. A scan without a good examination is just a picture without a story.
Step 2 · If Needed
Spine tests explained what each one shows
🧲 MRI (Magnetic Resonance Imaging)
🦴 X-ray
💠 CT Scan
🌡️ DEXA (Bone Density)
⚡ EMG / NCV (Nerve Studies)
🩸 Blood Tests & Bone Scan
Need a scan? We can guide you to trusted imaging and interpret it with your symptoms. Book a consultation →
Quick Comparison
MRI vs X-ray vs CT which do you need?
They answer different questions. X-ray for bones and alignment, MRI for discs, nerves and the spinal cord, CT for detailed bone and surgical planning. None is universally “better” — the right one depends on your symptoms.
| Test | Best at showing | Radiation | Typical use |
|---|---|---|---|
| X-ray | Bones, fractures, alignment | Low | Trauma, instability, first look |
| MRI | Discs, nerves, spinal cord, tumours | None | Sciatica, nerve pain, red flags |
| CT | Detailed bone anatomy | Higher | Complex fractures, surgical planning |
Practical Guide
Preparing for your spine scan
A little preparation makes your scan faster, more comfortable, and easier for your specialist to interpret correctly.
🧲 Before an MRI
Remove all metal (jewellery, hairpins, belts). Tell staff about any implants, pacemakers, cochlear implants or metal fragments — some are not MRI-safe. Mild claustrophobia? Ask about open MRI or a mild sedative option.
🦴 Before an X-ray or CT
Wear loose, metal-free clothing. Mention if you could be pregnant, since these use radiation. No fasting is usually needed unless a contrast dye is planned.
📁 What to bring
Any previous scans, reports or discharge summaries — even from years ago — help show what has changed. Bring a list of current medicines and a brief symptom timeline.
Most spine MRIs take 20–40 minutes depending on the region scanned. Results are typically ready the same day or within 24–48 hours, and are best discussed with a specialist rather than read in isolation.
Demystifying the Jargon
How to read your MRI / spine report
The disc has lost some water content — a normal part of ageing, seen in most adults.
The disc extends slightly beyond its normal edge; very common and often painless.
Disc protrusion / herniation
Inner disc material pushes outward; matters mainly if it presses a nerve matching your symptoms.
Annular tear / fissure
A small tear in the disc’s outer ring; common and frequently symptom-free.
Modic changes
Changes in the bone next to a disc; sometimes linked to pain, often not.
Wear/arthritis of the small spinal joints — common with age.
Narrowing of the space for the cord or nerves; significance depends on symptoms.
Age-related wear / a slipped vertebra — see our conditions guide.
A worrying-sounding report does not automatically mean a serious problem or surgery. What matters is whether the findings explain your symptoms — that’s a conversation for your specialist. Bring your report to a consultation →
When Reports Differ
Getting a second read on your scan or report
Radiology reports can occasionally differ between centres, or use technical language that’s hard to connect to your surgery recommendation. A second read is a normal, sensible step — not a sign of distrust.
📋 Bring the actual images
🔍 Ask what changed the plan
💬 A second opinion is normal
Especially before major surgery, reviewing your scans with an independent specialist is a reasonable, welcomed step.
When Imaging Is Urgent
When a scan shouldn't wait
Seek prompt imaging & specialist review if you have:
- Loss of bladder or bowel control, or saddle (groin) numbness — possible cauda equina
- Rapidly worsening or both-leg weakness, or foot drop
- Severe pain after a significant fall or accident (possible fracture)
- Back pain with fever, chills or unexplained weight loss (possible infection or tumour)
- A history of cancer with new, persistent back pain
Why NeuroWellness
The right test, read the right way
The value of a scan is in how it’s read – interpreted by a specialist, against your actual symptoms, not in isolation.
🧠 Neurosurgeon interpretation
Scans are interpreted by a neurosurgeon alongside your symptoms — not in isolation.
🧭 No unnecessary testing
We order a scan only when it will genuinely change your care — saving you time and cost.
📍 In Bengaluru
In-person and online consultations; bring existing scans for review, or get a second opinion.”
COMMON QUESTIONS
Spine Diagnosis & Imaging FAQs
Most short-term back pain does not need an MRI. Imaging is recommended when pain persists beyond about six weeks despite treatment, when there is radiating pain, numbness or weakness, or when red-flag signs suggest a serious cause such as infection, cancer, fracture or cauda equina. Diagnosis always begins with a clinical examination.
Often, no. Around 90% of back pain improves within a few weeks with simple care, and scanning too early can lead to unnecessary treatment. MRIs also show “abnormalities” like disc degeneration in many people with no pain at all, so findings must be matched to your symptoms by a specialist.
An X-ray shows bones, alignment and fractures. An MRI is the best test for soft tissues — discs, nerves and the spinal cord. A CT scan gives detailed bone imaging and is often used before surgery. They’re different tools for different questions, not one being universally “better”.
Not necessarily. Disc bulges and degeneration are extremely common and are frequently seen in people with no pain at all. What matters is whether the finding explains your specific symptoms — which is why a scan should always be interpreted alongside a clinical examination.
EMG (electromyography) and NCV (nerve conduction study) test how well your nerves and muscles are working. They help confirm whether a nerve is being compressed or damaged, and can distinguish a spine problem from other nerve conditions such as diabetic neuropathy or carpal tunnel syndrome.
Yes. Bring your existing MRI, CT or X-ray and reports to your consultation. We’ll interpret them alongside your symptoms — often that’s all that’s needed, with no repeat scanning. Second opinions are welcome.
For an MRI, remove all metal and tell the centre about any implants, pacemakers or metal fragments beforehand. For an X-ray or CT, wear loose, metal-free clothing and mention if you could be pregnant. Bring any previous scans, reports and a list of current medicines — this helps your specialist interpret the result correctly.
Yes, and it’s a normal, sensible step — especially before major surgery. Bring the actual scan images (not just the typed report) so a specialist can review them directly, and ask specifically which finding is driving any treatment recommendation.
Have a scan or symptoms? Get an expert read.
Bring your reports and existing scans or just your symptoms. You’ll get a clear, honest interpretation and a plan, without unnecessary testing.
Medically reviewed by Dr. Ganesh Veerabhadraiah, HOD and Senior Consultant Neurosurgeon, NeuroWellness, Bengaluru. Last reviewed: 21-Oct-2026
Disclaimer: This content is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Please consult a qualified specialist for guidance appropriate to your condition. Do not use this information for self-diagnosis or self-treatment. In a medical emergency, seek immediate care at the nearest hospital. NeuroWellness does not promote, endorse or recommend any particular doctor or procedure.